7 Advances in Heart Disease Treatment You Should Know About
Recent advances in heart disease treatment have transformed care in the past decade. Procedures that once required open-heart surgery can now be done through small catheters and minimally invasive techniques. Medications have extended and improved the lives of people with heart failure. In addition, new imaging can find heart disease earlier and more accurately than ever.
Here are seven advances in heart disease treatment that are changing outcomes for patients today, and what each could mean for you.
1. Modern Drug-Eluting Coronary Stents
A stent is a tiny mesh tube placed in a narrowed heart artery to keep it open. Early bare-metal stents often caused the artery to narrow again. Today’s drug-eluting stents slowly release medication that prevents scar tissue from growing inside the stent.
The newest generation uses thinner struts and coatings that dissolve over time. As a result, rates of re-narrowing and stent clotting are now low. Many patients can also take two blood thinners for a shorter time than in the past, which lowers bleeding risk. Researchers have found that, for some patients, one month of dual antiplatelet therapy can be safe after stent placement.
2. Intravascular Lithotripsy for Calcified Coronary Arteries
As people age, plaque in the heart arteries can harden with calcium, almost like bone. Coronary artery calcification makes it difficult to open the artery fully and expand a stent properly.
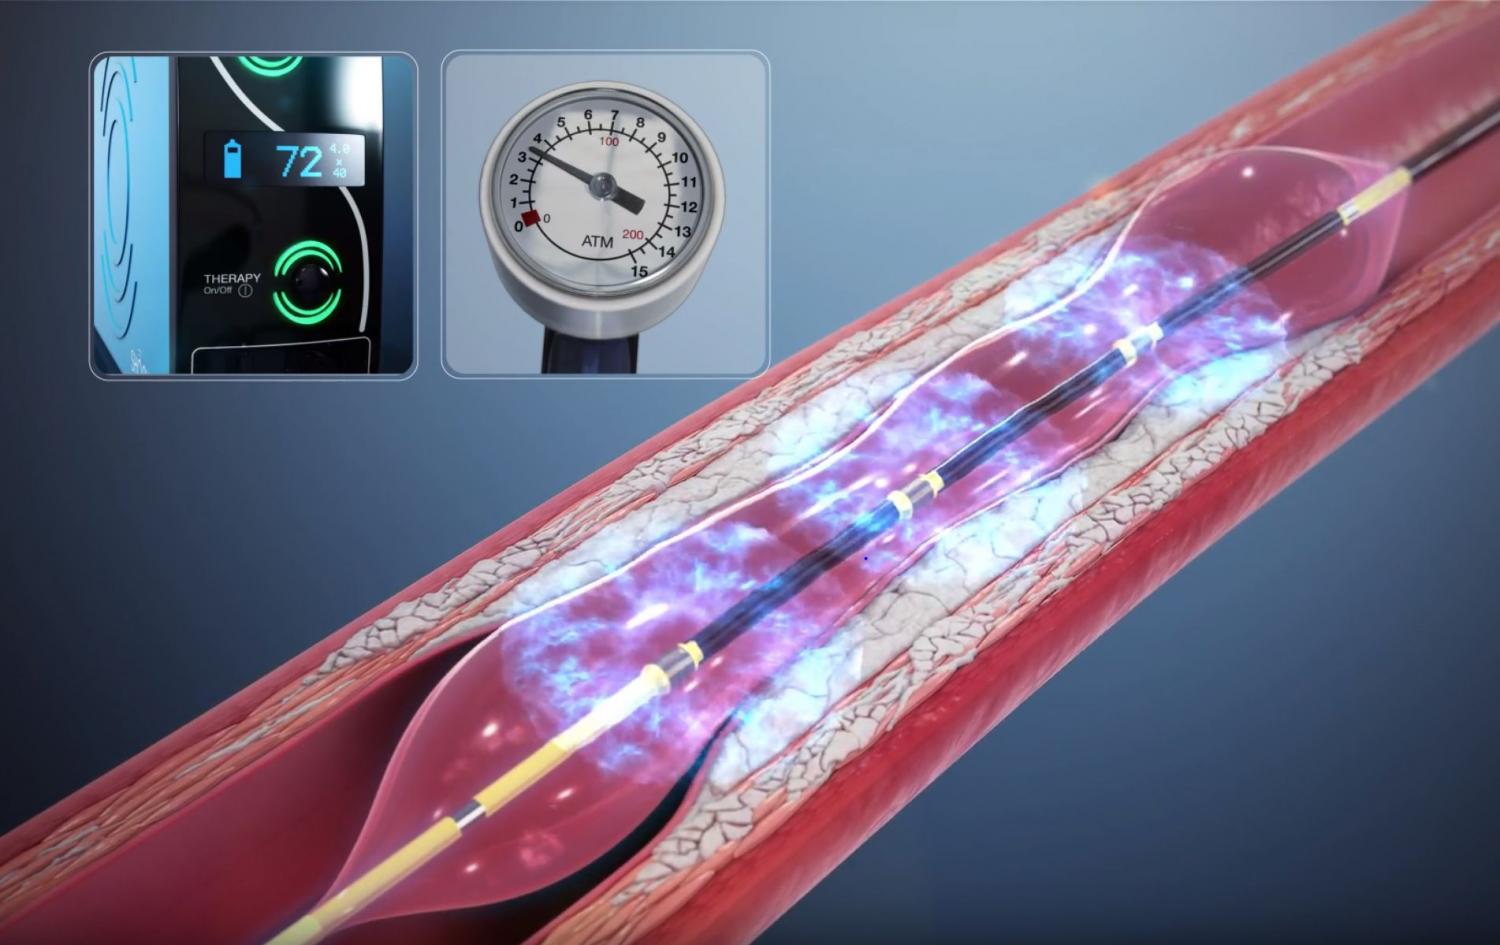
Intravascular lithotripsy (IVL) borrows technology used to break up kidney stones. A special balloon delivers sound-based pressure waves that crack the calcium inside the artery wall. The artery can then be opened and the stent fully expanded, with low rates of complications. For many patients with heavily calcified arteries, IVL has made catheter-based treatment possible where surgery once seemed like the only option. The American College of Cardiology reviews how IVL is used in contemporary practice.
3. Precision-Guided PCI With IVUS and OCT
Traditional angiograms show the outline of the artery on an X-ray, but not the artery wall itself. Intravascular imaging changes that:
- Intravascular ultrasound (IVUS) uses sound waves from a tiny probe inside the artery to measure plaque, vessel size and calcium.
- Optical coherence tomography (OCT) uses light to create very high-resolution images of the artery wall and the stent.
With these tools, cardiologists choose the right stent size, confirm it is fully expanded and check that its edges are well positioned. Studies show imaging-guided PCI reduces repeat procedures and heart events compared with angiography alone, particularly for complex blockages. Read the American College of Cardiology summary. For more on how these procedures help patients, see our post on the benefits of minimally invasive heart treatment.
4. Transcatheter Heart Valve Replacement (TAVR)
Aortic stenosis is a narrowing of the aortic valve that makes the heart work harder and can cause breathlessness, chest pain and fainting. In the past, the only replacement option was open-heart surgery.
With transcatheter aortic valve replacement (TAVR), a new valve is delivered through a catheter, usually from the groin, and placed inside the diseased valve. TAVR is now approved for patients across the full range of surgical risk. Many go home within one to two days. A heart team that includes an interventional cardiologist and a cardiac surgeon decides whether TAVR or surgery is the better option for each patient. Learn more about TAVR from NHLBI.
5. Newer Heart Failure Medications
Heart failure means the heart isn’t pumping or filling as well as it should. For people with a weakened heart muscle (heart failure with reduced ejection fraction), guidelines now recommend four classes of medication, often called the “four pillars”:
- ARNI therapy (sacubitril/valsartan, which relaxes blood vessel and reduces strain on the heart
- Beta-blockers, which slow the heart rate and protect the heart muscle
- Mineralicorticoid receptor antagonists (spironolactone, finerenone), which reduce fluid buildup and scarring
- SGLT2-inhibitors (such as dapagliflozin and empagliflozin, originally diabetes medications, that also protect the heart and kidneys, even in people without diabetes
Together, these medications lower the risk of hospitalization and death and can help the heart muscle recover. SGLT2-inhibitors also benefit many patients with heart failure with preserved ejection fraction, a form that once had few proven treatments. See the AHA’s guide to medications used to treat heart failure and the ACC’s key points from the heart failure guideline.

6. Coronary CT Angiography and CT-Derived FFR
Coronary CT angiography (CCTA) uses a fast CT scan and contrast dye to create detailed 3D images of the heart arteries, without a catheter. It can show both hard (calcified) and soft plaque, so heart disease can be found before it causes a heart attack.
CT-derived fractional flow reserve (FFR-CT) takes this further. Computer modeling of the CT images estimates whether a narrowing actually reduces blood flow. This helps identify who truly needs a catheter procedure and who can be treated with medication alone. National chest pain guidelines now support CCTA as a first-line test for many people with chest pain. The ACC reports that CT scanning is highly effective for evaluating chest pain. Some chest pain comes from conditions a CT scan can miss, such as microvascular disease, which we cover in 5 lesser-known heart conditions.

7. Leadless Pacemakers and Advanced Cardiac Devices
Traditional pacemakers sit under the skin of the chest and connect to the heart with wires called leads. Over time, leads and the pocket under the skin can cause problems such as infection or lead fracture.
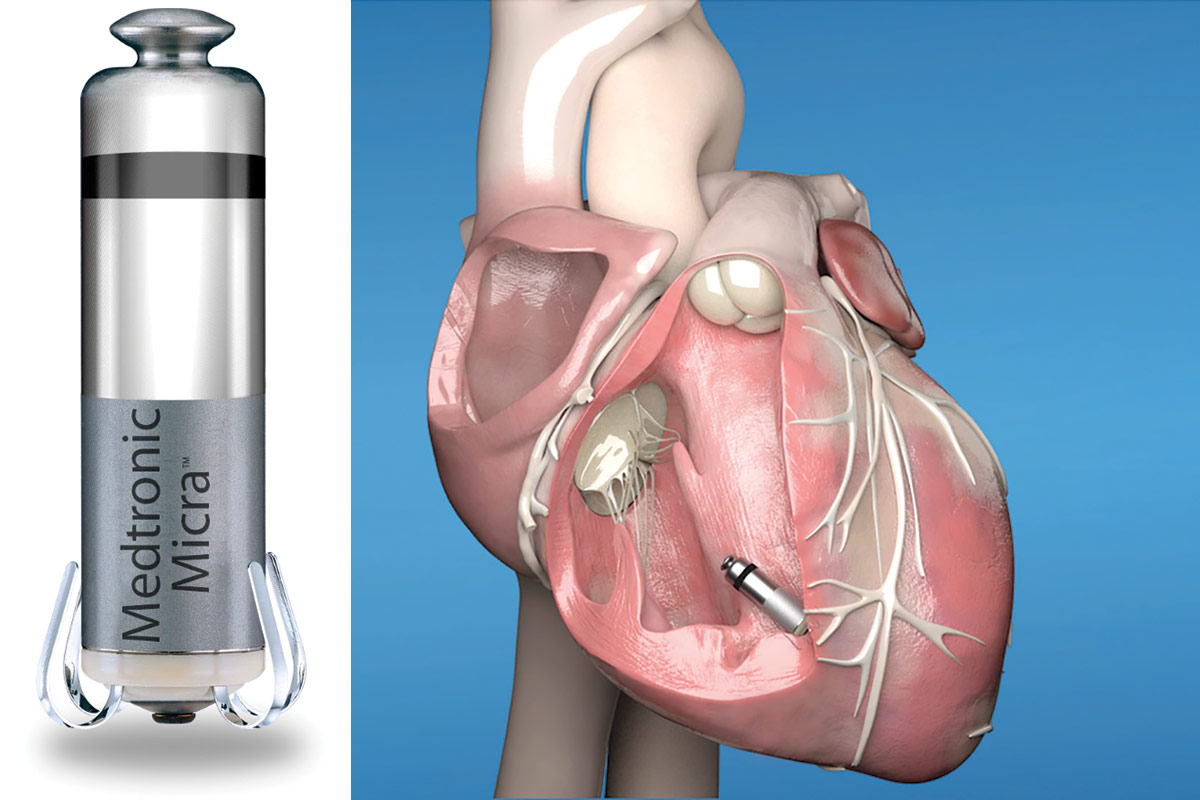
A leadless pacemaker is a self-contained device about the size of a large vitamin. It’s placed directly inside the heart through a catheter in the leg, so there’s no chest incision, no visible bump and no leads. Newer systems, such as the FDA-approved Aveir leadless pacing system, can now pace more than one chamber of the heart.
Other device advances include defibrillators that don’t need wires inside the heart and implantable monitors that track heart rhythm for years.

What These Advances in Heart Disease Treatment Mean for You
These advances give patients more options, faster recovery and more personalized care. However, the newest treatment isn’t always the right one. The best plan depends on your symptoms, test results, other health conditions and personal goals.
If you have symptoms such as chest pain, shortness of breath, palpitations or fainting, don’t wait. Review the 10 warning signs you should see a cardiologist and schedule an evaluation.
Frequently Asked Questions
Are drug-eluting stents safe long-term? Yes. Modern drug-eluting stents have strong long-term safety records and low rates of re-narrowing. Taking your prescribed blood thinners and controlling cholesterol, blood pressure and diabetes helps keep them working.
Who is a candidate for TAVR? TAVR is approved for people with severe aortic stenosis across all levels of surgical risk. A heart team considers your age, anatomy, overall health and preferences to decide between TAVR and surgery.
Can heart failure improve with medication? Yes. With today’s guideline-recommended medications, many people with heart failure feel better, have fewer hospital stays and see their heart function improve, sometimes significantly.
Is a coronary CT angiogram better than a stress test? They answer different questions. A coronary CT angiogram shows the arteries and plaque directly, while a stress test shows how the heart performs under exertion. Your cardiologist will recommend the right test for your situation.
How long does a leadless pacemaker battery last? Battery life depends on how often the device paces, but it typically lasts many years. When the battery runs low, a new device can usually be added or the old one retrieved, depending on the system.
Access Advanced Heart Care in Tampa
Our board-certified interventional cardiologist offers modern, evidence-based heart care, from advanced imaging and echocardiography to catheter-based procedures at Tampa General Hospital and St. Joseph’s Hospital. We’ll explain your options clearly and build a plan around you.
Request an appointment or call (813) 540-4322.
602 S Audubon Ave, Suite A, Tampa, FL 33609
Medical Disclaimer
The content provided on the Ascent Cardiology website is intended for general educational and informational purposes only. The information, articles, and media presented on this website do not constitute medical advice, diagnosis, or treatment recommendations. Content published on this website is not intended to replace consultation, evaluation, or treatment by qualified healthcare professionals, including the providers at Ascent Cardiology or other licensed medical professionals.
If you believe you may be experiencing a medical emergency, call 911 or seek immediate emergency medical care.
The medical information, opinions, and educational materials presented on this website are provided for general awareness and may not reflect the specific clinical practices or medical opinions of Ascent Cardiology or its providers. Reliance on any information provided on this website is solely at your own risk.
This website may include links to third-party medical or educational websites for informational purposes only. Ascent Cardiology does not control, endorse, or assume responsibility for the accuracy, reliability, or content of any third-party websites linked from this site.
Sources
- What Is a Stent? — American Heart Association
- One Month of Dual Antiplatelet Therapy Is Safe and Feasible After Stent Placement — AHA Newsroom
- Coronary Artery Calcification — Cleveland Clinic
- Shocking the Rock With Coronary Intravascular Lithotripsy in Contemporary Practice — American College of Cardiology
- Intravascular Imaging-Guided PCI vs. Angiography-Guided PCI — American College of Cardiology
- What Is TAVR? — American Heart Association
- Transcatheter Aortic Valve Replacement — NHLBI
- Medications Used to Treat Heart Failure — American Heart Association
- 2022 AHA/ACC/HFSA Heart Failure Guideline: Key Perspectives — American College of Cardiology
- CT Scan Is Most Effective to Assess People With Chest Pain — American College of Cardiology
- Is a Leadless Pacemaker Right for You? — Cleveland Clinic
- Aveir Leadless Pacing System — U.S. Food and Drug Administration

Heart Testing Before Organ Transplant: Things Every Patient Should Know
If you’re being evaluated for a kidney or liver transplant, you’ve probably been told you need “cardiac clearance.” For many
Autoimmune Diseases and Heart Disease: Hidden Risks You Should Know
If you live with lupus, rheumatoid arthritis, psoriasis, or another autoimmune condition, your care probably focuses on your joints, skin,

Varicose Vein Treatment: RFA vs. VenaSeal – 7 Things You Should Know
Aching, heavy legs. Swelling by the end of the day. Bulging, twisted veins you’d rather hide in shorts weather. If
7 Benefits of Minimally Invasive Heart Treatment
Not long ago, treating a blocked heart artery or a failing valve almost always meant open-heart surgery. Today, minimally invasive heart treatment lets interventional cardiologists treat many of these conditions through a tiny puncture in the wrist or groin. Patients often go home the same day or the next morning.
The most common of these procedures is percutaneous coronary intervention (PCI), also called angioplasty and stenting. Other catheter-based treatments include transcatheter valve replacement and procedures for complex blockages. Here are seven benefits of this approach and what they mean for you.
1. Minimally Invasive Treatment Without Open-Heart Surgery
Traditional bypass surgery requires opening the breastbone and often stopping the heart. In contrast, minimally invasive heart treatment is performed through a thin, flexible tube called a catheter. The catheter is guided through an artery in the wrist (radial artery) or upper thigh (femoral artery) to the heart.
Most patients receive local anesthesia and light sedation rather than general anesthesia. There’s no large incision, no cut breastbone and no heart-lung machine. As a result, the procedure is easier on the body, especially for older adults and people with other health conditions. Learn what happens during a cardiac catheterization from the Society for Cardiovascular Angiography and Interventions.
2. Faster Recovery and Shorter Hospital Stays
Recovery is one of the biggest differences between catheter-based treatment and surgery.
- After angioplasty and stenting: Many patients go home the same day or after one night. Most return to normal activities within about a week.
- After open-heart surgery: A hospital stay of several days is typical, and full recovery often takes 6 to 12 weeks.
Wrist (radial) access has made recovery even easier. Compared with groin access, it lowers bleeding risk and lets patients sit up and walk soon after the procedure. See Cleveland Clinic’s guide to recovering after angioplasty and stenting.
3. Improved Blood Flow to the Heart
Coronary artery disease narrows the arteries that supply the heart with oxygen-rich blood. During angioplasty, a small balloon opens the narrowed artery. Then a stent, a tiny mesh tube, is placed to hold it open. Modern drug-eluting stents slowly release medicine that helps keep the artery from narrowing again.
Restoring blood flow lets the heart muscle get the oxygen it needs, especially during exercise. For patients with severe or high-risk blockages, this can also protect heart function over time.
4. Life-Saving Treatment During a Heart Attack
During a major heart attack, a blood clot completely blocks a coronary artery and heart muscle begins to die within minutes. Emergency angioplasty, known as primary PCI, is the preferred way to reopen the artery quickly. National guidelines aim to open the artery within 90 minutes of arriving at the hospital.
The faster blood flow returns, the more heart muscle is saved. That leads to better long-term heart function and survival. Read more about heart attack treatment from the American Heart Association. Women’s heart attack symptoms can be subtle, so also review our guide to women’s heart attack symptoms.
5. Relief of Angina and Improved Quality of Life
Angina is chest pain or pressure caused by reduced blood flow to the heart. It can make walking, climbing stairs or exercising uncomfortable or frightening. Medications are the first step for stable angina. However, when symptoms continue despite medication, angioplasty and stenting can provide significant relief.
Many patients find they can walk farther, return to activities they had given up, and rely on fewer medications for chest pain. Learn more about angina treatment options from NHLBI.
6. Advanced Precision With Modern Imaging Technology
Today’s interventional cardiologists don’t rely on X-ray pictures alone. Advanced tools show the inside of the artery and measure how much a blockage actually limits blood flow:
- Intravascular ultrasound (IVUS) and optical coherence tomography (OCT) show the artery wall from the inside, so stents can be sized and positioned precisely.
- Fractional flow reserve (FFR) and related pressure measurements show whether a narrowing is truly reducing blood flow, which helps avoid unnecessary stents.
For complex blockages, imaging-guided PCI has been linked to fewer repeat procedures and better outcomes than angiography alone. Read a summary of intravascular imaging-guided PCI research from the American College of Cardiology.
7. Individualized Treatment for Complex Cardiovascular Conditions
Minimally invasive heart treatment is no longer only for simple blockages. Catheter-based options now include:
- Complex PCI for heavily calcified arteries, blockages where arteries branch, and chronic total occlusions
- Transcatheter aortic valve replacement (TAVR) for severe aortic stenosis
- Peripheral interventions to restore blood flow to the legs
No single treatment is right for everyone. Your cardiologist will weigh your symptoms, anatomy, other health conditions and goals. For some patients, medication alone or bypass surgery is the better choice. When surgery may be the right option, an interventional cardiologist works with a cardiac surgeon as part of a heart team.
Who Is a Candidate for Minimally Invasive Heart Treatment?
You may be a candidate if you have:
- Chest pain or shortness of breath that continues despite medication
- An abnormal stress test or coronary CT scan showing significant blockages
- A heart attack or unstable angina
- Severe aortic stenosis, which may be treated with TAVR
- Leg pain when walking caused by blocked arteries
The first step is a thorough evaluation, which may include a stress test, echocardiogram, coronary CT angiography or diagnostic catheterization. Not sure whether your symptoms need attention? Read 10 warning signs you should see a cardiologist. Some chest pain comes from conditions that don’t need a stent, such as coronary microvascular dysfunction. Learn about these in our post on lesser-known heart conditions.
Frequently Asked Questions
Is angioplasty painful? Most patients feel only a brief pinch when the numbing medicine is given at the wrist or groin. You’ll be awake but relaxed with light sedation. Some people feel brief chest pressure while the balloon is inflated.
How long does a stent last? Stents are designed to stay in place permanently. Modern drug-eluting stents have low rates of re-narrowing. Taking your prescribed blood thinners and managing cholesterol, blood pressure and diabetes helps protect the stent and your other arteries.
How soon can I return to work after a stent? Many people with desk jobs return within a few days to a week after a planned procedure. Recovery after a heart attack usually takes longer, and cardiac rehabilitation is recommended.
Is minimally invasive heart treatment safe? Angioplasty and stenting are among the most commonly performed heart procedures, and serious complications are uncommon. Your cardiologist will review your individual risks and benefits before the procedure.
When is open-heart surgery the better choice? Bypass surgery may be better for some patients with blockages in several arteries, particularly those with diabetes or reduced heart function. Your cardiologist and a cardiac surgeon can review your case together to recommend the best option.
Explore Minimally Invasive Heart Treatment in Tampa
Our board-certified interventional cardiologist performs advanced, catheter-based heart procedures at Tampa General Hospital and St. Joseph’s Hospital. Every treatment plan starts with a thorough evaluation and a clear explanation of your options.
Request an appointment or call (813) 540-4322.
602 S Audubon Ave, Suite A, Tampa, FL 33609
Medical Disclaimer
The content provided on the Ascent Cardiology website is intended for general educational and informational purposes only. The information, articles, and media presented on this website do not constitute medical advice, diagnosis, or treatment recommendations. Content published on this website is not intended to replace consultation, evaluation, or treatment by qualified healthcare professionals, including the providers at Ascent Cardiology or other licensed medical professionals.
If you believe you may be experiencing a medical emergency, call 911 or seek immediate emergency medical care.
The medical information, opinions, and educational materials presented on this website are provided for general awareness and may not reflect the specific clinical practices or medical opinions of Ascent Cardiology or its providers. Reliance on any information provided on this website is solely at your own risk.
This website may include links to third-party medical or educational websites for informational purposes only. Ascent Cardiology does not control, endorse, or assume responsibility for the accuracy, reliability, or content of any third-party websites linked from this site.
Sources
- Percutaneous Coronary Intervention — NHLBI
- Stents: Getting a Stent — NHLBI
- Angina Treatment — NHLBI
- Angiogram/Cardiac Catheterization — SCAI SecondsCount
- After Your Interventional Procedure — Cleveland Clinic
- Heart Attack Treatment — American Heart Association
- Angina (Chest Pain) — American Heart Association
- What Is TAVR? — American Heart Association
- Intravascular Imaging-Guided PCI vs. Angiography-Guided PCI — American College of Cardiology

Heart Testing Before Organ Transplant: Things Every Patient Should Know
If you’re being evaluated for a kidney or liver transplant, you’ve probably been told you need “cardiac clearance.” For many

Autoimmune Diseases and Heart Disease: Hidden Risks You Should Know
If you live with lupus, rheumatoid arthritis, psoriasis, or another autoimmune condition, your care probably focuses on your joints, skin,

Varicose Vein Treatment: RFA vs. VenaSeal – 7 Things You Should Know
Aching, heavy legs. Swelling by the end of the day. Bulging, twisted veins you’d rather hide in shorts weather. If
5 Lesser-Known Heart Conditions: Symptoms You Shouldn’t Ignore
When most people think of heart disease, they picture blocked arteries and heart attacks. However, several lesser-known heart conditions cause real symptoms and are often missed for years. Some don’t show up on routine tests. Others mimic common problems like anxiety, asthma or aging.
Knowing these conditions can help you speak up when something doesn’t feel right. Here are five worth knowing, the symptoms to watch for, and how they’re diagnosed and treated.
1. Coronary Microvascular Dysfunction (CMD)
What it is: CMD affects the heart’s tiniest blood vessels rather than the large coronary arteries. These small vessels don’t widen properly, so the heart muscle doesn’t get enough blood during exertion or stress. Because the large arteries look normal, patients are often told their heart is “fine.”
Symptoms to watch for:
- Chest pain or pressure, often lasting longer than typical angina
- Chest pain during daily activities or emotional stress
- Shortness of breath and fatigue
- Trouble sleeping
Who’s at risk: CMD is more common in women, especially around and after menopause. High blood pressure, diabetes and high cholesterol also raise risk. Women’s heart symptoms often differ from men’s, so read our guide to women’s heart attack symptoms.
Diagnosis and treatment: CMD is diagnosed with specialized tests, including cardiac PET, stress cardiac MRI or coronary function testing in the cath lab. Treatment typically includes medications to relax blood vessels and control blood pressure, plus statins and lifestyle changes. Learn more about coronary microvascular disease from the American Heart Association.
2. Takotsubo Cardiomyopathy (Broken Heart Syndrome)
What it is: Takotsubo cardiomyopathy is a sudden, temporary weakening of the heart muscle. It is usually triggered by intense emotional or physical stress, such as the death of a loved one, a frightening event or a serious illness. A surge of stress hormones “stuns” the heart, and the main pumping chamber balloons out at the tip.
Symptoms to watch for:
- Sudden chest pain
- Shortness of breath
- Symptoms that look exactly like a heart attack
Who’s at risk: About 90% of cases occur in women, most often after menopause.
Diagnosis and treatment: Because broken heart syndrome mimics a heart attack, it needs emergency care. Doctors confirm it with a cardiac catheterization showing no major blockages, along with an echocardiogram showing the typical shape. Most people recover heart function within weeks with medications and monitoring. Read more about broken heart syndrome from Harvard Health.
3. Hypertrophic Cardiomyopathy (HCM)
What it is: HCM is an inherited condition in which the heart muscle becomes abnormally thick. The thickened muscle can block blood flow out of the heart and make it stiff. HCM affects about 1 in 500 people, yet many don’t know they have it.
Symptoms to watch for:
- Shortness of breath, especially with exercise
- Chest pain
- Dizziness or fainting, particularly during or right after exercise
- Palpitations
- A heart murmur found on exam
Who’s at risk: Anyone with a parent, sibling or child with HCM, since each child of an affected parent has a 50% chance of inheriting it. HCM is also a leading cause of sudden cardiac death in young athletes.
Diagnosis and treatment: An echocardiogram is the key test, often with cardiac MRI and genetic testing. Treatment has advanced significantly. Options include beta blockers, newer cardiac myosin inhibitors, septal reduction procedures and implantable defibrillators for high-risk patients. Learn more about hypertrophic cardiomyopathy from the AHA.
4. Cardiac Amyloidosis
What it is: In cardiac amyloidosis, abnormal proteins called amyloid build up in the heart muscle and make it stiff. The most common form in older adults is transthyretin (ATTR) amyloidosis, which can be age-related or inherited. Once considered rare, it is now recognized as an underdiagnosed cause of heart failure.
Symptoms to watch for:
- Shortness of breath and fatigue
- Swelling in the legs, ankles or abdomen
- Dizziness when standing, or low blood pressure in someone who used to have high blood pressure
- Carpal tunnel syndrome in both wrists, often years before heart symptoms
- Spinal stenosis or a ruptured biceps tendon
- Numbness or tingling in the hands and feet
Who’s at risk: Men over 60 are most often affected. The inherited V122I variant is more common in people of African descent.
Diagnosis and treatment: Diagnosis often starts with an echocardiogram showing thickened heart walls. A nuclear PYP scan and blood and urine tests can then confirm ATTR amyloidosis without a biopsy in many patients. New medications can stabilize or reduce the abnormal protein and slow progression, so early diagnosis matters. See the signs and symptoms of cardiac amyloidosis from CardioSmart, the American College of Cardiology’s patient site.
5. Myocardial Bridging
What it is: Normally the coronary arteries run along the surface of the heart. In myocardial bridging, a section of artery, usually the left anterior descending (LAD) artery, tunnels through the heart muscle instead. Each time the heart contracts, the muscle “bridge” squeezes the artery.
Symptoms to watch for:
- Chest pain during exercise
- Shortness of breath
- Fatigue or reduced exercise tolerance
- Palpitations
Most people with a myocardial bridge have no symptoms. In some, though, it can reduce blood flow enough to cause angina, even in young and otherwise healthy people.
Diagnosis and treatment: Myocardial bridging is found with coronary CT angiography or cardiac catheterization, sometimes with specialized pressure testing. Many patients do well with beta blockers or calcium channel blockers. Surgery is reserved for severe cases that don’t respond to medication. Learn more about myocardial bridges from Cleveland Clinic.
When to See a Cardiologist About Lesser-Known Heart Conditions
These conditions are easy to miss because their symptoms overlap with more common problems. See a cardiologist if you have:
- Chest pain that continues even after a “normal” stress test or angiogram
- Fainting or near-fainting with exercise
- Shortness of breath or fatigue that keeps getting worse
- Carpal tunnel in both wrists along with heart failure symptoms
- A family history of HCM or sudden cardiac death
For a broader checklist, read 10 warning signs you should see a cardiologist.
Call 911 for sudden chest pain, severe shortness of breath or fainting. Several of these conditions, including broken heart syndrome, look exactly like a heart attack, and only emergency testing can tell them apart.
Frequently Asked Questions
Can you have chest pain with clear coronary arteries? Yes. Coronary microvascular dysfunction, myocardial bridging and coronary artery spasm can all cause chest pain even when a standard angiogram looks normal. Specialized testing can find the cause.
Can stress really cause heart damage? Yes. Takotsubo cardiomyopathy, or broken heart syndrome, is triggered by severe emotional or physical stress. The heart usually recovers fully, but it requires emergency care and follow-up.
Is hypertrophic cardiomyopathy genetic? Yes. HCM is usually inherited. If a close family member has HCM, your cardiologist may recommend an echocardiogram and genetic counseling for you and your children.
Why is carpal tunnel linked to heart disease? The same amyloid protein that stiffens the heart in ATTR amyloidosis can build up in the wrists. Carpal tunnel in both hands can appear 5 to 10 years before heart symptoms, making it an important early clue.
Are these heart conditions treatable? Yes. Each has effective treatments, from medications to procedures. Newer therapies for HCM and cardiac amyloidosis have significantly improved outcomes when the conditions are caught early.
Get Answers About Your Heart Symptoms in Tampa
If your symptoms haven’t been explained, or you’ve been told your heart is “normal” but you still don’t feel right, a specialist evaluation can help. Our board-certified interventional cardiologist uses advanced imaging, including echocardiography, to diagnose lesser-known heart conditions and build a personalized treatment plan.
Request an appointment or call (813) 540-4322.
602 S Audubon Ave, Suite A, Tampa, FL 33609
If you are having chest pain, severe shortness of breath or fainting, call 911.
This article is for educational purposes only and is not a substitute for professional medical advice, diagnosis or treatment.
Medical Disclaimer
The content provided on the Ascent Cardiology website is intended for general educational and informational purposes only. The information, articles, and media presented on this website do not constitute medical advice, diagnosis, or treatment recommendations. Content published on this website is not intended to replace consultation, evaluation, or treatment by qualified healthcare professionals, including the providers at Ascent Cardiology or other licensed medical professionals.
If you believe you may be experiencing a medical emergency, call 911 or seek immediate emergency medical care.
The medical information, opinions, and educational materials presented on this website are provided for general awareness and may not reflect the specific clinical practices or medical opinions of Ascent Cardiology or its providers. Reliance on any information provided on this website is solely at your own risk.
This website may include links to third-party medical or educational websites for informational purposes only. Ascent Cardiology does not control, endorse, or assume responsibility for the accuracy, reliability, or content of any third-party websites linked from this site.
Sources
- Coronary Microvascular Disease — American Heart Association
- Coronary Microvascular Dysfunction: What Clinicians and Investigators Should Know — NIH/PMC
- Takotsubo Cardiomyopathy (Broken-Heart Syndrome) — Harvard Health
- Hypertrophic Cardiomyopathy — American Heart Association
- 2024 AHA/ACC Guideline for the Management of Hypertrophic Cardiomyopathy
- Cardiac Amyloidosis Signs and Symptoms — CardioSmart (ACC)
- Myocardial Bridge — Cleveland Clinic

Heart Testing Before Organ Transplant: Things Every Patient Should Know
If you’re being evaluated for a kidney or liver transplant, you’ve probably been told you need “cardiac clearance.” For many

Autoimmune Diseases and Heart Disease: Hidden Risks You Should Know
If you live with lupus, rheumatoid arthritis, psoriasis, or another autoimmune condition, your care probably focuses on your joints, skin,

Varicose Vein Treatment: RFA vs. VenaSeal – 7 Things You Should Know
Aching, heavy legs. Swelling by the end of the day. Bulging, twisted veins you’d rather hide in shorts weather. If